
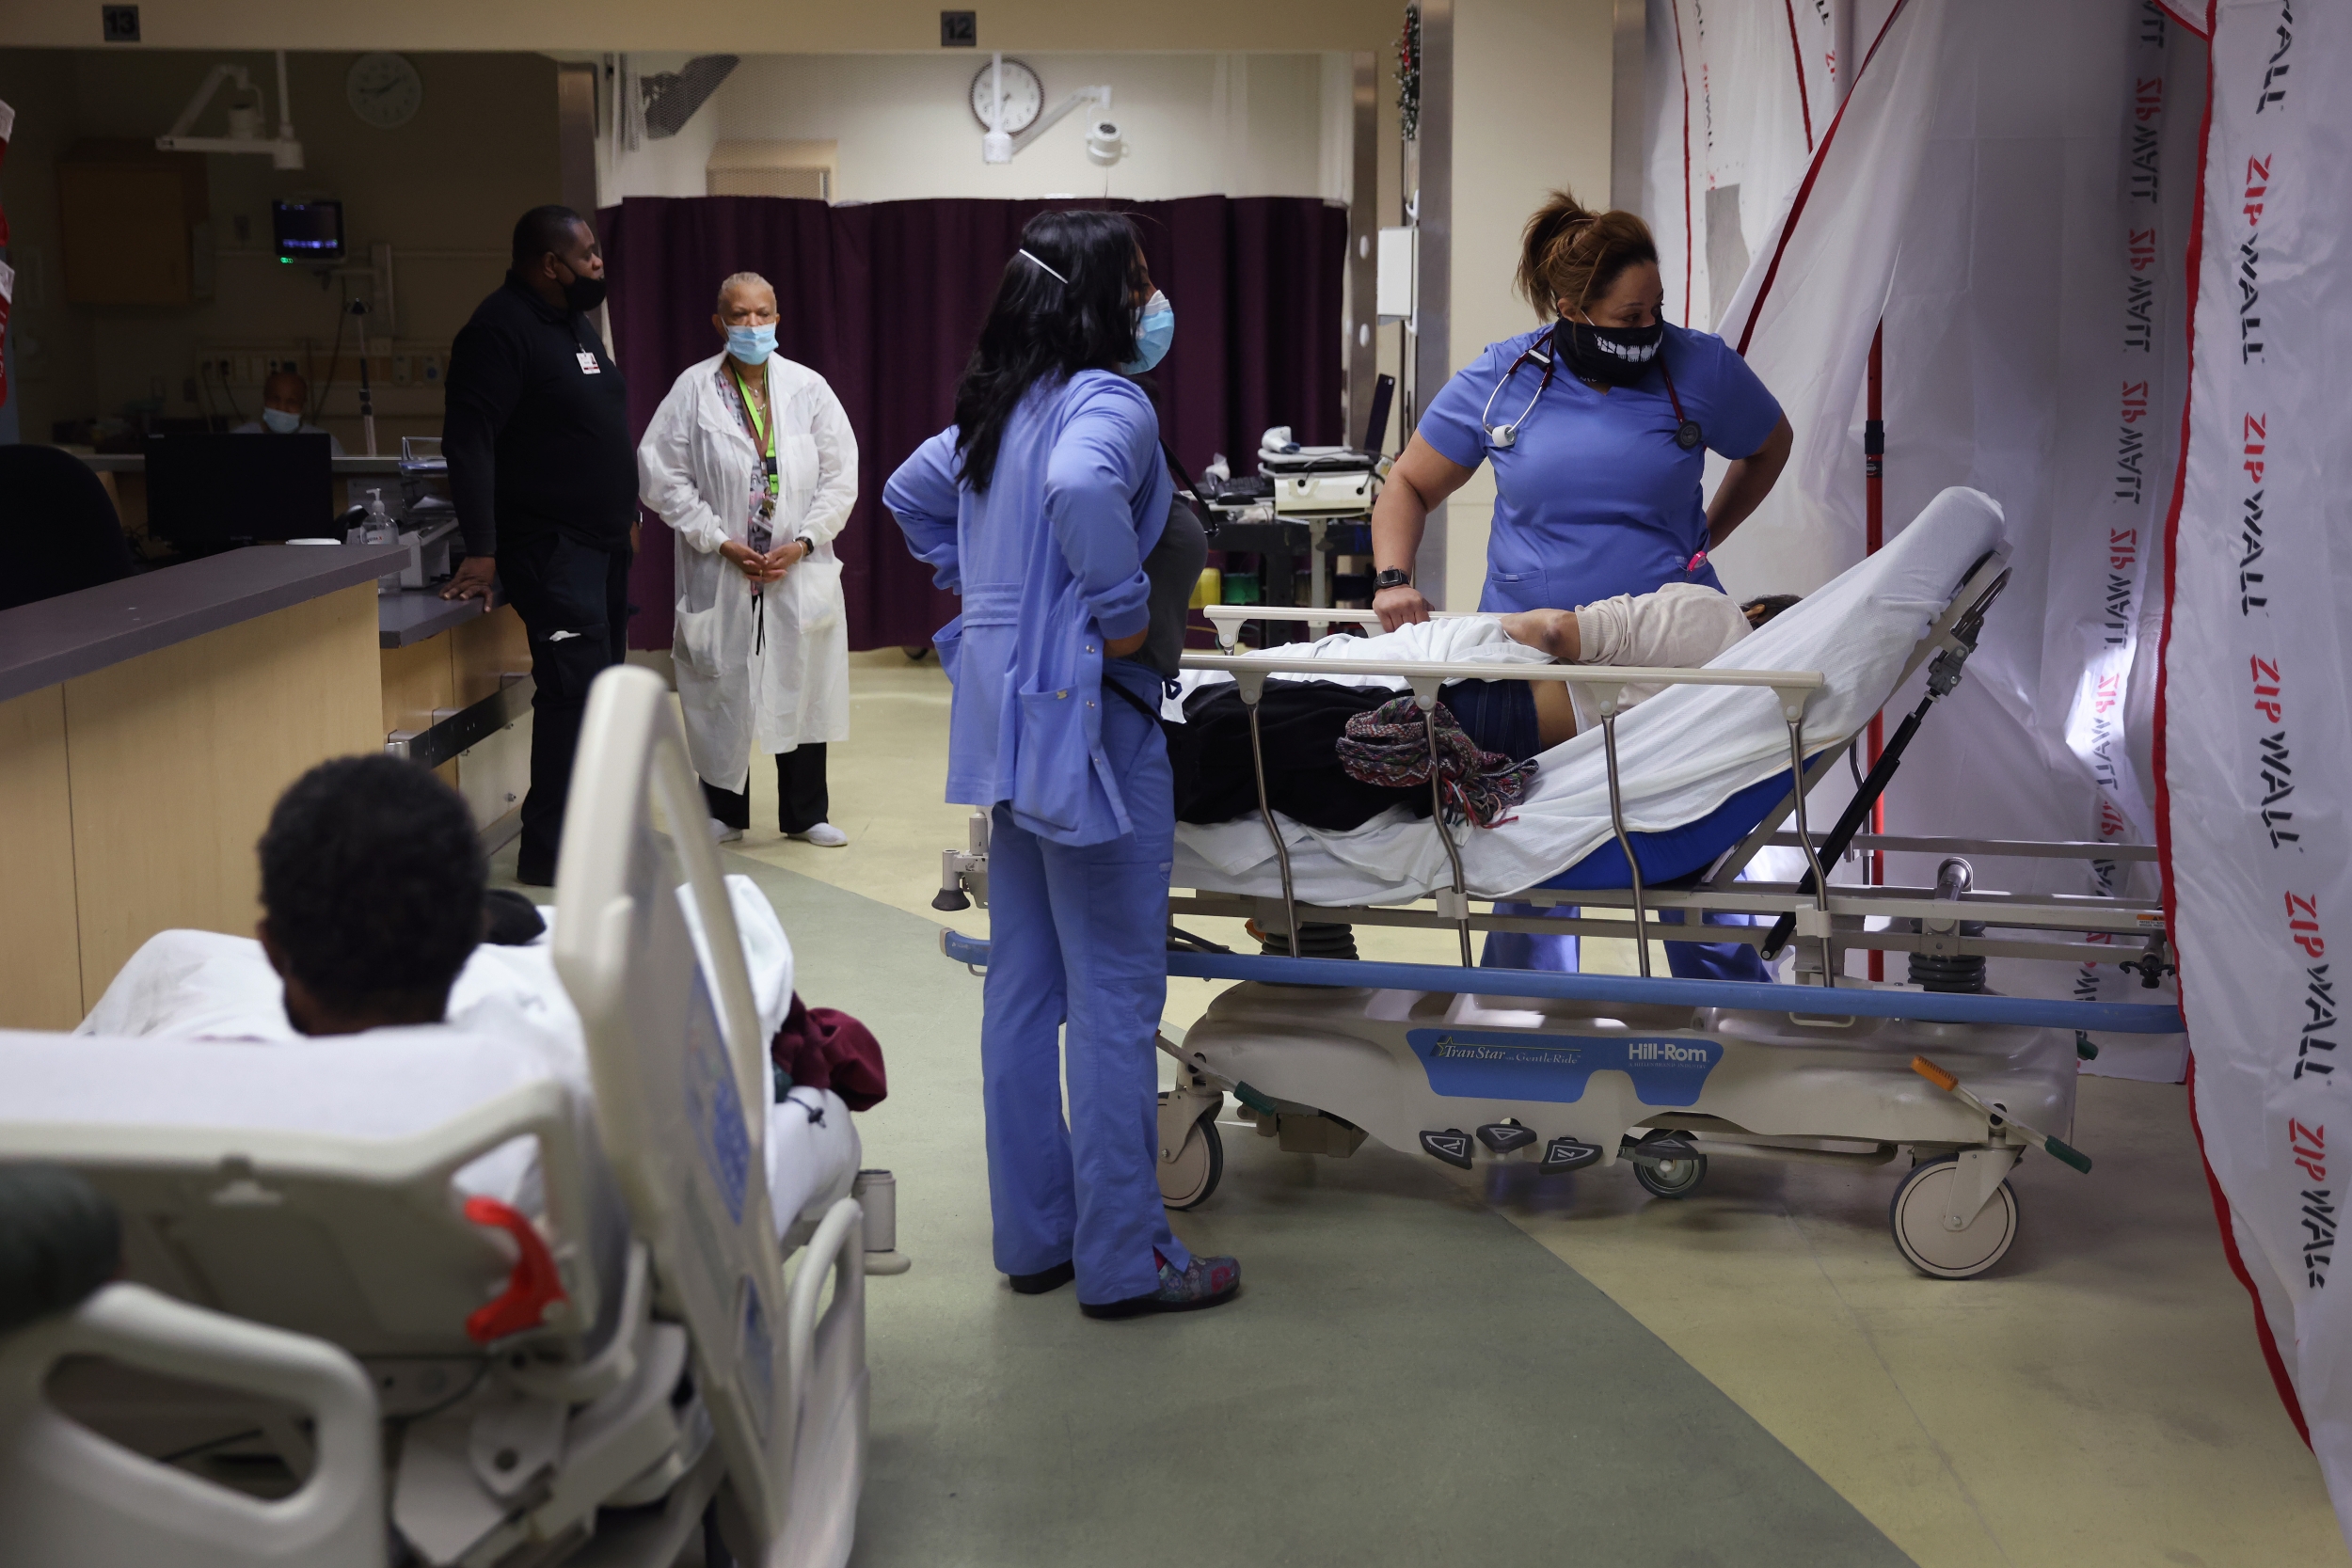
The pennsylvania measles outbreak is intensifying as a high-stakes dispute between state health officials and the Centers for Disease Control and Prevention (CDC) erupts over the official reporting of four measles-associated deaths.
Key Takeaways
- Growing Discrepancy: Pennsylvania has reported four measles-associated deaths, while the CDC’s national mortality tally currently lists zero.
- Escalating Numbers: There are 731 confirmed measles cases across 38 Pennsylvania counties, with 141 hospitalizations reported.
- Political Conflict: A significant standoff has emerged between Pennsylvania Governor Josh Shapiro and U.S. Health and Human Services (HHS) Secretary Robert F. Kennedy Jr. over the validity of the outbreak data.
- Clinical Shifts: Medical professionals are reporting “new forms” of the disease, including congenital measles in newborns.
- Aggressive Response: The state has established over 140 pop-up clinics to increase MMR vaccination rates amid the surge.
- Monitor Symptoms: Watch for fever, cough, runny nose, and red, watery eyes. A rash typically follows, starting on the head and spreading downward. Symptoms often appear 7 to 21 days after exposure.
- Urgent Care Protocol: If you suspect measles, do not walk directly into a clinic or emergency room. Because measles is highly airborne and can remain infectious in a room for up to two hours, you must call ahead to notify providers so they can take isolation precautions.
- Vaccination Access: Ensure children are up to date on the MMR (measles, mumps, and rubella) vaccine. The two-dose schedule provides approximately 97% lifetime protection. Uninsured families may be eligible for free vaccines through the federal “Vaccines for Children” program.
- Testing Readiness: Pennsylvania has implemented a 24-hour turnaround time for measles testing to facilitate rapid contact tracing.
- Isolation Protocols: Maintain strict airborne precautions for any patient presenting with suspicious symptoms to prevent nosocomial spread.
- The Causality Gap: How can the CDC and state health departments reconcile the difference between “measles-associated” and “measles-caused” deaths in a way that is transparent to the public?
- Data Integrity vs. Speed: Does the CDC’s insistence on exhaustive pathological review (as seen in the Lancaster County spleen case) hinder the ability to respond to an accelerating outbreak?
- Political Interference: To what extent is the tension between Governor Shapiro and Secretary Kennedy influencing the technical communication between the DOH and HHS?
- The Undercount Risk: If many infected individuals are staying home without testing, what is the true scale of the transmission within Pennsylvania’s 38 affected counties?
- CDC Review Results: The federal government’s decision on whether to include the four Pennsylvania deaths in the national tally will be a critical indicator of how mortality data will be handled moving forward.
- Epi-Aid Deployment: Whether the CDC accepts the state’s request for disease detectives will dictate the level of federal support available for contact tracing and containment.
- Vaccination Trends: Health officials will be monitoring whether the surge in MMR administration (which rose from a monthly average of 25,000 to 46,000 doses in August) is sufficient to reach herd immunity thresholds.
- Long-term Clinical Monitoring: Specialists will continue to monitor the impact of congenital measles cases on newborn health outcomes.
- www.medicaldaily.com
- www.nbcphiladelphia.com
- local21news.com
- www.theguardian.com
What Happened
The Pennsylvania measles outbreak has moved beyond a localized health concern into a federal-state political standoff. As of late September 2026, Pennsylvania has confirmed 731 cases of measles, a number that infectious disease specialists warn is likely an undercount due to patients remaining at home without seeking medical testing.
On Friday, September 19, 2026, the CDC updated its national measles dashboard, but notably excluded four deaths reported by the Pennsylvania Department of Health (DOH). The state maintains these deaths are measles-associated, citing clinical evidence and positive laboratory tests. However, the CDC is withholding these figures pending a thorough review of the circumstances and underlying causes of death.
This reporting gap has triggered a request from members of Congress for an “immediate briefing” on the decision to change how measles deaths are reported. The tension is compounded by a conditional request from Pennsylvania State Health Secretary Debra Bogen for an “Epi-Aid”—the deployment of CDC disease detectives—stating that the state would withdraw the request unless the CDC publicly acknowledges the four reported deaths. In response, the CDC has accused the state of engaging in “political blackmail.”
Why It Matters
The discrepancy in death reporting is more than a procedural disagreement; it impacts public trust and the perceived severity of the outbreak. When official federal numbers do not align with state-level data, it can create confusion regarding the actual risk to the community.
For the medical community, the stakes are even higher. Dr. John Goldman, an infectious disease specialist at the University of Pittsburgh Medical Center, warned that the outbreak appears to be “accelerating.” He noted that the medical landscape is changing as providers encounter cases that were previously exceedingly rare, such as congenital measles—where infants contract the virus in utero or at birth.
Furthermore, the accuracy of these numbers dictates how resources are allocated. If the CDC does not recognize the severity of the mortality rate in Pennsylvania, the deployment of critical federal epidemiological support may be delayed, potentially allowing the virus to spread further through unvaccinated populations.
Deep-Dive: The Data Discrepancy and Clinical Reality
To understand the conflict, one must look at the differing methodologies used by state and federal agencies to classify a “measles death.”
The Definition Debate
Currently, the CDC is working with the Council of State and Territorial Epidemiologists to establish a standardized definition for measles deaths. Until that is finalized, the agency relies on data from the National Center for Health Statistics (NCHS), which identifies measles as the underlying cause based on state-submitted death records.
However, recent investigations by local officials have complicated the state’s narrative. For instance, the Lancaster County Coroner clarified that of the two initial deaths reported by the state in late August, one involved an infant who died from a lacerated spleen rather than the measles virus itself. While the infant had tested positive for measles, the coroner’s office maintains the virus was not the cause of death. This distinction between dying with measles and dying from measles is at the heart of the CDC’s cautious approach.
Outbreak Statistics at a Glance
The following table summarizes the reported data as of mid-September 2026:
| Metric | Pennsylvania State Count | CDC National Tally |
|---|---|---|
| Total Confirmed Cases | 731 | 2,903 (U.S. Total) |
| Hospitalizations | 141 | Not Specified |
| Reported Deaths | 4 | 0 |
| Affected Counties | 38 | N/A |
| Vaccination Status of Deaths | 100% Unvaccinated | N/A |

Stakeholders and Reactions
The Pennsylvania measles outbreak has become a lightning rod for political friction between state and federal leadership.
State Leadership
Governor Josh Shapiro has characterized the outbreak as a “deeply serious” situation and has defended the state’s transparency. He has also been a vocal critic of federal skepticism, accusing HHS Secretary Robert F. Kennedy Jr. of engaging in “fearmongering” and “conspiracy theories” regarding the validity of the reported deaths.
Secretary Debra Bogen has taken an aggressive stance, linking the state’s request for federal epidemiological aid directly to the CDC’s recognition of the deaths. “The CDC’s choice not to publicly recognize the deaths undermines our response,” Bogen stated.
Federal Leadership
CDC Director Erica Schwartz has denied that deaths are being miscounted for political reasons, instead attributing the delay to the rigorous process of establishing a mortality definition. She compared the situation to COVID-19 reporting, noting that officials must distinguish between a person having a virus and that virus being the actual cause of death.
HHS Secretary Robert F. Kennedy Jr. has expressed significant skepticism. During a recent speech, he cast doubt on whether the reported deaths actually occurred and suggested that the attention given to measles deaths should be balanced with scrutiny of vaccine side effects. His comments have been met with sharp criticism from state officials.
Clinical Insights: The ‘Canary in the Coal Mine’
For clinicians on the front lines, the current outbreak represents a significant departure from the last several decades of American medicine. Dr. John Goldman, who had not seen a single case of measles between 1992 and 2026, noted that he is now seeing at least one case every day.
Goldman expressed concern that measles may be a “canary in the coal mine” for other vaccine-preventable diseases, such as whooping cough, diphtheria, and polio. The emergence of congenital measles is particularly concerning to specialists, as it presents a clinical challenge for which there is limited long-term data.
What It Means for You
If you are a resident of Pennsylvania or any area experiencing an increase in respiratory illnesses, the following practical implications and guidance apply:
For Parents and Caregivers
For Healthcare Providers
Counterpoints and Open Questions
While the state’s urgency is clear, several questions remain unanswered that complicate the public health response:
What Happens Next
Several key developments will determine the trajectory of the Pennsylvania measles outbreak in the coming months:
Frequently Asked Questions
Why is there a difference between the state and CDC death counts?
The discrepancy stems from different classification standards. Pennsylvania uses a “measles-associated” definition that includes clinical evidence and positive tests. The CDC requires more definitive proof that measles was the primary cause of death, rather than a secondary factor or a coincidental infection. For example, in one case, a coroner found the death was actually caused by a ruptured spleen, leading the CDC to exclude it from the official measles death toll.
How contagious is measles?
Measles is one of the most contagious diseases known to medicine. It is an airborne virus that can linger in the air or on surfaces for up to two hours after an infected person has left the area. This high level of transmissibility is why the Pennsylvania measles outbreak has spread across 38 counties so rapidly.
How effective is the MMR vaccine?
According to state health reports, the two-dose MMR vaccination schedule provides approximately 97% lifetime protection against measles. In the current outbreak, the vast majority of those who have died were unvaccinated, while breakthrough cases among the vaccinated have remained rare and generally did not require hospitalization.
What should I do if I think I have been exposed?
If you believe you have been exposed, contact your healthcare provider by phone immediately. Do not visit a medical facility in person without calling first, as measles is highly infectious and can easily spread in waiting rooms. Follow all isolation instructions provided by health officials to prevent further community transmission.
As the Pennsylvania measles outbreak continues to evolve, the tension between rigorous scientific verification and the need for rapid public health action remains the central challenge for both state and federal authorities.
References
Featured image: Image via Medical Daily

